
Introduction
Proximal humerus fractures (PHFs) are a common injury, particularly in the older age group, and represent a significant portion of orthopedic trauma cases. These fractures account for approximately 10% of all fractures in individuals aged 65 and older.1,2 With the increase in life expectancy and aging populations worldwide, the incidence of PHFs should increase significantly in the coming decades. PHFs are often associated with high morbidity, primarily due to their impact on shoulder mobility, which is critical for performing activities of daily living.3–6
The treatment of PHFs remains a subject of debate, with options ranging from conservative management to surgical intervention. Surgical treatment options include osteosynthesis (using plates or intramedullary nails) and shoulder arthroplasty (reverse shoulder arthroplasty [RSA], arthroplasty, or hemiarthroplasty).7 Each technique has specific indications depending on the patient’s age, fracture type, and bone quality. However, no clear consensus has been reached on the optimal surgical approach for complex PHFs, particularly Neer III, IV, and VI fractures.
Osteosynthesis is traditionally preferred in younger patients due to its ability to preserve bone stock and the potential for fracture healing. However, complications, such as non-union, malunion, and avascular necrosis are concerns, particularly in older patients with poor bone quality and a decreased union rate. Arthroplasty, particularly RSA, has gained popularity in recent years, as it circumvents some of these complications and enables early mobilization, resulting in favorable functional outcomes.8,9 It has been refined over the years,10 and more studies have compared its use to hemiarthroplasty,11,12 examined different implants,13–15 or investigated primary versus conversion RSA.16 Despite the increasing use of RSA, there is a lack of high-quality studies17 comparing functional outcomes, particularly range of motion (ROM), between osteosynthesis and RSA in PHFs.18–24 This study aimed to address this gap by comparing active ROM at 6-12 months post-operatively in patients treated with osteosynthesis versus arthroplasty (RSA or hemiarthroplasty) at a high-volume orthopedic center in Mexico City, to determine which implant presents the best functional outcomes for PHFs.
Material and methods
Study design
This is a retrospective, comparative cohort study conducted at the Instituto Nacional de Rehabilitación Luis Guillermo Ibarra Ibarra. The study included patients treated for PHFs between January 2016 and January 2023.
Patient selection
Patients were included if they met the inclusion criteria: age between 50 and 80 years.
Diagnosed with a Neer III, IV, or VI PHF.
Underwent surgical treatment with either osteosynthesis or shoulder arthroplasty (hemiarthroplasty or RSA).
Available follow-up data at 6 and 12 months post-operatively.
Patients were excluded if they had pre-existing shoulder pathologies (e.g., advanced osteoarthritis), a history of previous shoulder surgeries, or incomplete follow-up data.
Data collection
Patient data, including demographics, fracture classification (Neer), surgical technique, and ROM measurements, were collected from electronic medical records by the authors and peer-reviewed by shoulder surgeons at our Institution. ROM was assessed using a goniometer at the Institute’s outpatient clinic. It included flexion, extension, abduction, external rotation at neutral abduction, internal rotation in adduction (graded by the vertebral level reached by the thumb), and adduction at 90° with the patient lying in a supine position.
Statistical analysis
All statistical analyses were conducted using the Statistical Package for the Social Sciences version 25. Parametric data were analyzed using Student’s t-test for continuous variables and the chi-square test for categorical variables. Analysis of variance was used to compare ROM outcomes between groups at each time point. A p < 0.05 was considered statistically significant.
Results
A total of 108 patient records were reviewed. Of these, 52 patients were excluded because they did not meet the inclusion criteria due to incomplete follow-up data, resulting in a final cohort of 56 patients. The cohort was divided into two treatment groups: 45 patients underwent osteosynthesis (36 with intramedullary nails and 9 with plates), and 11 patients underwent shoulder arthroplasty (6 with RSA and 5 with hemiarthroplasty).
Demographic
The mean age of the patients was 67.05 years. The osteosynthesis group had a mean age of 67.33 years, and the arthroplasty group had a mean age of 65.9 years. For the osteosynthesis group, the mean age for patients with plates was 66.33, and for those with nails, 67.58. For the arthroplasty group, RSA patients had a mean age of 67.16, and hemiarthroplasty patients had a mean age of 64.4 years. The cohort included 41 women (37 underwent osteosynthesis and 4 underwent arthroplasty) and 15 men (8 underwent osteosynthesis and 7 underwent arthroplasty).
ROM outcomes: at 6 months post-operatively, the arthroplasty group demonstrated superior ROM in all measured categories compared to the osteosynthesis group. The mean flexion for the arthroplasty group was 114.54° compared to 105.15° in the osteosynthesis group. Similar trends were observed for extension (40.9° vs. 37°), abduction (105.45° vs. 90.49°), and external rotation (24.1° vs. 19.7°) (Fig. 1).
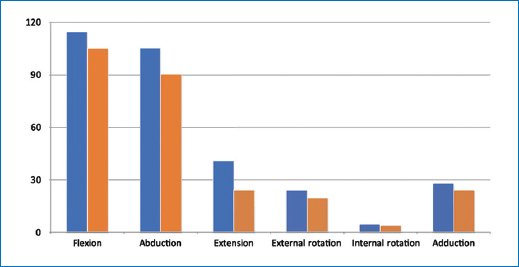
Figure 1. Range of motion at 6 months for arthroplasty (shown in blue) and osteosynthesis (shown in orange), p < 0.001.
At 12 months, patients treated with arthroplasty continued to exhibit superior ROM outcomes. Flexion in the arthroplasty group was 135°, compared to 132.06° in the osteosynthesis group. Notably, the differences in external rotation diminished, with osteosynthesis patients showing slightly better outcomes (34.15° for osteosynthesis vs. 31.82° for arthroplasty). However, arthroplasty maintained an advantage in internal rotation, with patients achieving an average vertebral level of L1-L2, whereas patients with osteosynthesis averaged between L2 and L3. The findings were consistent for adduction, with arthroplasty patients reaching 45.45° compared to 40.46° in the osteosynthesis group (Fig. 2).
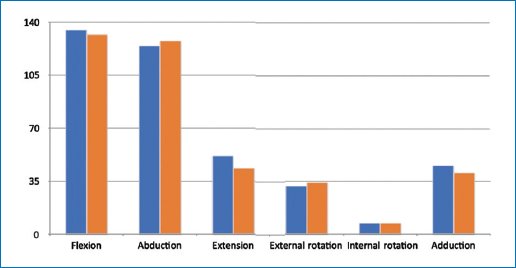
Figure 2. Range of motion at 12 months for arthroplasty (shown in blue) and osteosynthesis (shown in orange), p < 0.001.
A breakdown of the surgical subtypes (RSA, hemiarthroplasty, and osteosynthesis with plates or nails) revealed that RSA provided the best overall functional recovery. At 6 months, patients treated with RSA had an average flexion of 123.3°, significantly higher than the 104° in patients with hemiarthroplasty, 106.6° in patients treated with intramedullary nails, and 114.5° in those treated with plates (Fig. 3).
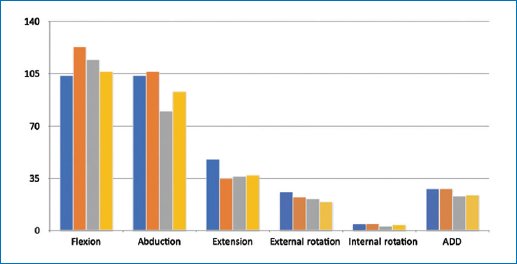
Figure 3. Range of motion at 6 months for hemiarthroplasty (shown in blue), reverse shoulder arthroplasty (shown in orange), plate osteosynthesis (shown in grey) and intramedullary nail (shown in yellow), p < 0.001.
At 12 months, flexion improved further in the RSA group, reaching 144°, whereas those treated with hemiarthroplasty reached 124°, intramedullary nails reached 135.66° and with plates, 117.8°. In terms of abduction, RSA patients reached 130° at 12 months, compared to 118° in the arthroplasty group, 132.9° in the osteosynthesis group treated with nails, and 107.2° in those treated with plates. External rotation was higher in the osteosynthesis group (34.2° for nails and 33.9° for plates) compared to 30° in the RSA patients, with the arthroplasty group reaching 34°. Internal rotation was better in RSA patients, with an average vertebral level of L2 at 12 months, compared to L3 for the osteosynthesis group (Fig. 4).
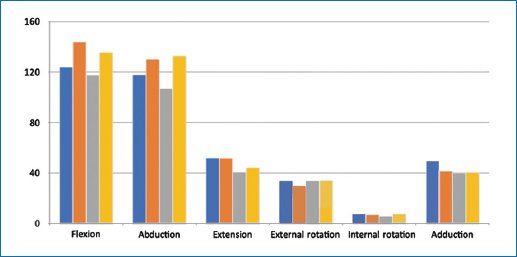
Figure 4. Range of motion at 12 months for hemiarthroplasty (shown in blue), reverse shoulder arthroplasty (shown in orange), plate osteosynthesis (shown in grey) and intramedullary nail (shown in yellow), p < 0.001.
The study reported only one patient in the osteosynthesis group experiencing a complication (a revision surgery for surgical site infection). No complications were reported in the arthroplasty group, highlighting the safety and efficacy of both RSA and hemiarthroplasty in this patient population, reinforcing previously published studies.9,25 A longer follow-up could be beneficial in the RSA group to exclude other complications, such as scapula fracture and implant loosening.26,27
Discussion
The results of this study support the use of arthroplasty, specifically RSA, for the treatment of PHFs, particularly in older patients or those with complex fractures, such as Neer III and IV. RSA provided superior outcomes in active ROM at both 6 and 12 months post-operatively. These findings are consistent with the growing body of literature suggesting that RSA is a highly effective treatment modality for PHFs.
RSA is advantageous in cases where the rotator cuff is compromised, as it relies on the deltoid muscle to restore function, particularly for flexion and abduction. The design of RSA compensates for the loss of rotator cuff function, allowing patients to achieve good ROM and functional recovery at 6 and 12 months. Our findings corroborate those of previous studies, which have demonstrated that RSA yields better functional outcomes and lower complication rates compared to osteosynthesis.
At 6 months, RSA patients exhibited greater flexion and abduction compared to those treated with osteosynthesis. These results reflect the early mobilization and rapid functional recovery associated with arthroplasty. By 12 months, RSA continued to outperform osteosynthesis in flexion, internal rotation, and adduction. While osteosynthesis provided slightly better results in external rotation, this was an expected outcome given that RSA does not fully restore the function of the rotator cuff.
Osteosynthesis
Osteosynthesis remains a viable treatment option, particularly for younger patients or those with less complex fractures. The ability to preserve bone stock and achieve anatomical reduction makes osteosynthesis appealing in selected cases. The inherent limitations of this approach, including the potential for non-union, malunion, and post-traumatic arthritis, must be considered. In our study, patients treated with osteosynthesis showed good outcomes, particularly in external rotation and abduction at 12 months. This can be attributed to the preservation of the rotator cuff and the restoration of normal shoulder mechanics.
However, RSA demonstrated better overall ROM, particularly in flexion and internal rotation, supporting its use in patients requiring faster recovery and better functional outcomes. In addition, the non-complication rate associated with RSA in our study underscores its safety and efficacy, particularly in older populations.
A comparison with recent studies shows that our results align well with the present literature regarding the use of RSA for treating PHFs. Guo et al.,7 Fraser et al.,8 Chalmers et al.,21 and Suroto et al.23 reported superior outcomes in ROM and lower complication rates for RSA, particularly in older patients with complex fractures. These studies reinforce the evidence that RSA is a highly effective option for patients with complex PHFs, especially in older populations or those with significant rotator cuff damage.
Studies by Alrabaa et al.27 and Papalia et al.28 demonstrate a migration of preference for using RSA over OSS in patients with PHF, since complications are lower and functional outcomes have become better and more predictable for RSA over the years. Furthermore, as stated by Freeman et al.,29 hemiarthroplasty for PFH treatment is decreasingly used as it is inversely proportional to the use of RSA.
This study has some limitations. As a retrospective study, it inherently limits the control over variables. It increases the potential for selection bias, which was mitigated in our study as no patients who met all the inclusion and exclusion criteria were eliminated. In addition, the sample size was relatively small, specifically in the arthroplasty group (although bigger than most of the studies searched for the purpose of this study), which may limit the generalizability of the findings. Further, the study only included patients treated at a single center.
Despite these limitations, the study provides valuable insights into the comparative outcomes of RSA and osteosynthesis in PHFs, particularly in Mexican population. Future prospective studies with a larger population and multi-center participation are needed to validate these results further.
Conclusion
The results of this study suggest that RSA is an effective treatment option for PHFs, particularly Neer III, IV, and VI fractures, in patients aged 50-80. RSA provides superior functional outcomes in ROM at both 6 and 12 months post-operatively, particularly in flexion, internal rotation, and adduction. Although osteosynthesis remains a viable option for less complex fracture patterns and younger patients, RSA offers a faster recovery and better overall functional outcomes in patients with complex fractures.
Given the growing body of evidence supporting the use of RSA in PHFs, it is recommended as the treatment of choice in older patients or those requiring a quicker return to daily activities. Osteosynthesis, particularly with intramedullary nails, remains an excellent alternative, especially for patients who have good bone stock and simple fractures. Future studies could focus on longer-term outcomes and further explore the role of RSA in young people with PHFs, specifically how the components age in a patient who, for the most part, has a more active lifestyle than those typically treated with RSA. In addition, future studies that combine isolated movements (similar to our study) with functional questionnaires could yield promising findings for a more comprehensive analysis of disability.
Funding
The authors declare that they have not received funding.
Conflicts of interest
The authors declare no conflicts of interest.
Ethical considerations
Protection of human subjects and animals. The authors declare that no experiments on humans or animals were performed for this research.
Confidentiality, Informed Consent, and Ethical Approval. The authors have obtained approval from the institute’s Ethics and Research Committee on August 18th, 2024, under the registration number INRLGII 49/24, for the analysis of routinely collected and anonymized clinical data; therefore, individual informed consent was not required. Relevant ethical recommendations have been followed.
Declaration on the use of artificial intelligence. The authors declare that no generative artificial intelligence was used in the writing or creation of the content of this manuscript.
