
Introduction
In 1994, the film Forrest Gump was released, starring actor Tom Hanks. The character possessed incredible kinesthetic adaptability, which enabled him to develop physical skills such as running, as well as the focus and concentration needed to play ping pong or reload weapons very quickly – all of which were caused by hypermetabolism, that is, an acceleration in the functioning of different cells in the body. As with exercise and stress, among other factors, burn injuries involving more than 20% of the total body surface area trigger an inflammatory and subsequent hypermetabolic response driven by supraphysiological elevations of stress hormones, catecholamines, and inflammatory mediators that begins immediately after the burn injury and may persist for years; for this reason, we draw a homology with hypermetabolism, calling it Forrest Gump syndrome.1
Endogenous catecholamines are primary mediators of the hypermetabolic response to burns. This systemic response is characterized by the development of a hyperdynamic circulation, an increase in basal energy expenditure, and catabolism of muscle protein.2
Initially, cardiac function is depressed in response to the impact of the injury. However, 48-72 h after the injury, heart rate (HR) and cardiac output increase to meet the body’s greater oxygen demand. In addition to these changes, patients with severe burns experience loss of muscle mass3 and a 40-80% increase in metabolic rate.4 Consequently, the structure and function of essential organs such as muscle, skin, the heart, the immune system, and the liver are compromised, contributing to multiple organ failure, sepsis, and mortality5 (Fig. 1).
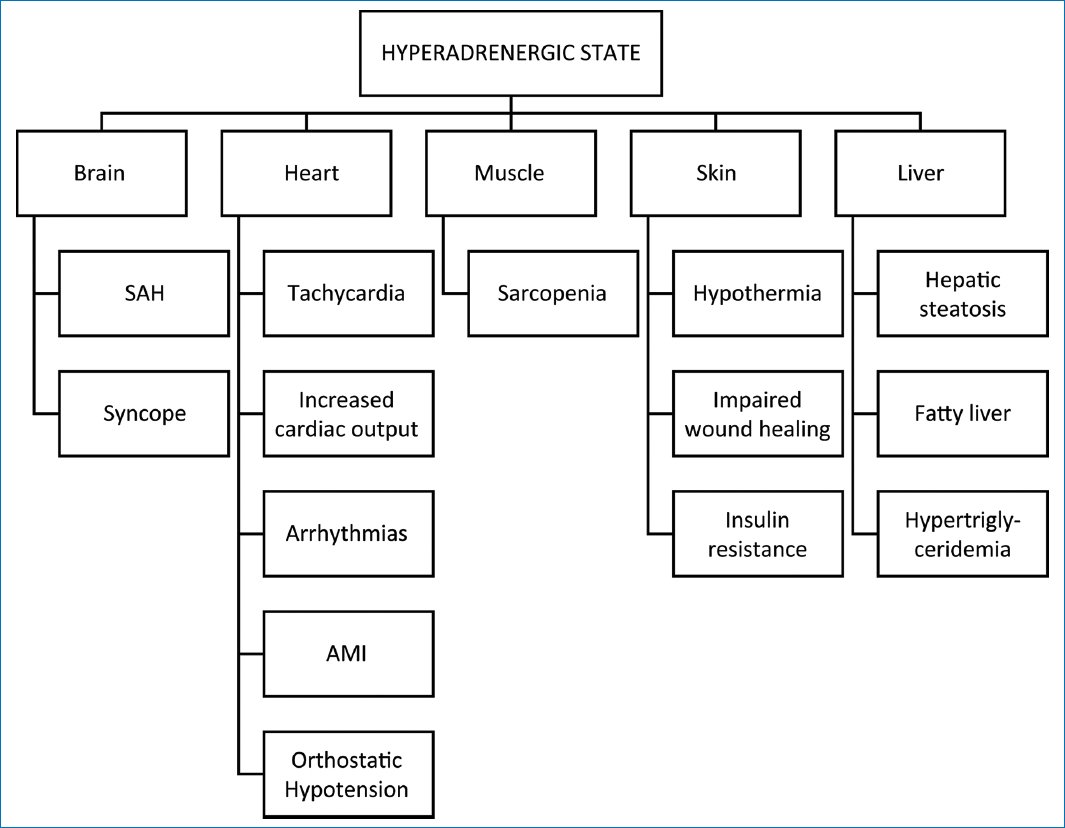
Figure 1. Different types of organ-level repercussions of the hyperadrenergic state.
Hypermetabolic response
Hypermetabolism is accompanied by increased muscle catabolism to provide nutrients that meet the body’s elevated energy requirements. As a consequence, hypermetabolism can lead to multiorgan dysfunction or even death. Metabolic and inflammatory changes persist for up to 3 years after the injury. The duration and magnitude of the hypermetabolic response are major determinants of morbidity in the burn patient. The prolonged catabolic response results in bodily changes such as loss of muscle mass and bone mineral content, which slow the recovery of these patients and their reintegration into society2 (Fig. 2).
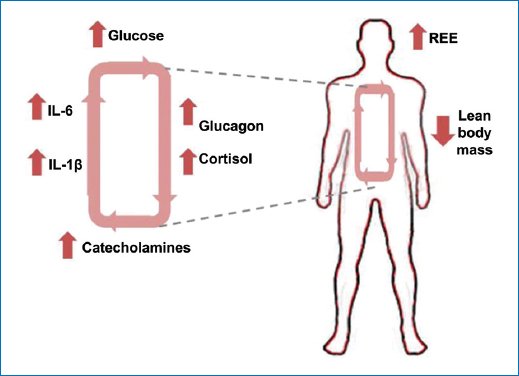
Figure 2. Physiology of hypermetabolism. IL-6: interleukin-6; IL-1β: interleukin-1 beta; REE: resting energy expenditure.
The hypermetabolic state has two aspects: the “ebb” and “flow” phases. The ebb phase, which occurs within the first 48 h after injury, is associated with a decrease in cardiac output, oxygen consumption, and metabolic rate. The chronic flow phase is critical and requires medical intervention to reduce the risk of fatal outcomes.1
In the flow phase, increased energy expenditure is observed, which is associated with catabolism of muscle proteins, alterations in hepatic protein synthesis, and loss of peripheral fat stores by inducing the degradation of lipids into free fatty acids and glycerol.6
Pathophysiology of hypercatabolism in the burn patient
The hypermetabolic response is characterized by increased peripheral lipolysis, increased muscle wasting, elevated HR, elevated cardiac output, and increased body temperature, among other features.
Skeletal muscle metabolism, represented by the degradation of muscle fibers, primarily provides a major source of energy substrates to support wound healing, maintain temperature, and activate the immune system. Muscle catabolism persists after wound closure; episodes of sarcopenia have been described up to 3 years after the burn injury.7
This will result in increased resting energy expenditure, rapid muscle loss, development of sarcopenia, frailty, and malnutrition, as well as an increase in the incidence of depression, anxiety, and post-traumatic stress disorder, which will delay healing and rehabilitation and predispose patients to a greater risk of infections.
Recovery
At present, propranolol, a beta-blocker, is one of the treatments used to attenuate the effects of hypercatabolism and the deleterious effects of elevated catecholamine levels8 (Table 1).
Table 1. Systemic effects of propranolol according to its pathophysiology
| Pathophysiology and particularities of the burn patient | Effects of propranolol in the burn patient |
|---|---|
| Primary mediators of the hypermetabolic response: catecholamines | Non-selective blockade of β-adrenergic receptors |
| Hyperdynamic circulation and increased cardiac output | Decreases heart rate and cardiac workload |
| Increased basal energy expenditure | Decreases supraphysiological thermogenesis and resting energy expenditure |
| Increased muscle protein catabolism | Promotes recycling of intracellular free amino acids in muscle; Stimulates expression of genes involved in muscle metabolism and decreases activation of genes involved in gluconeogenesis, thereby reducing net catabolism |
| Increased peripheral lipolysis; Hepatic fat accumulation | Decreases peripheral lipolysis; Increases hepatic efficiency in secreting free fatty acids; Decreases mesenteric blood flow |
| Need for healing of burns and graft donor sites | Higher fractional protein synthesis rate in the wound; Increased efficiency of use of amino acids from wound catabolism to synthesize new proteins; Higher protein deposition rate and free amino acid concentrations in the wound; Improvement of healing and epithelialization |
| In sepsis, increased monocytosis with suppression of monocyte inflammatory response | Reduction of sepsis-induced monocytosis in burn patients, increased percentage of inflammatory monocytes, granulocytosis, and tumor necrosis factor-α production |
| Predominance of M2 subtype monocytes with reduced antibacterial capacity |
Since the late 1980s, researchers have analyzed the use of propranolol, a non-selective β-adrenergic receptor blocker, to mitigate the action of catecholamines after burn injury, successfully reducing HR, myocardial oxygen consumption, and resting energy expenditure in patients with severe burns.3,8
Propranolol
In 1958, Sir James Black discovered a drug – the first beta-blocker approved for clinical use – propranolol, a prototype of the first-generation beta-blockers, which are drugs with similar affinities for AR-β1 and β2 receptors, and for this reason are considered “non-selective beta-blockers.” In 1966, in the search for derivatives capable of avoiding the bronchodilatory effect of propranolol in patients with asthma (due to its β2 antagonist activity), the team at Imperial Chemical Industries introduced practolol, the first representative compound of second-generation beta-blockers – drugs that show greater affinity for AR-β1 than for β2 and are considered “β1-selective” or “cardioselective beta-blockers” due to the predominant presence of the β1 subtype in the heart9 (Fig. 3 and Table 2).
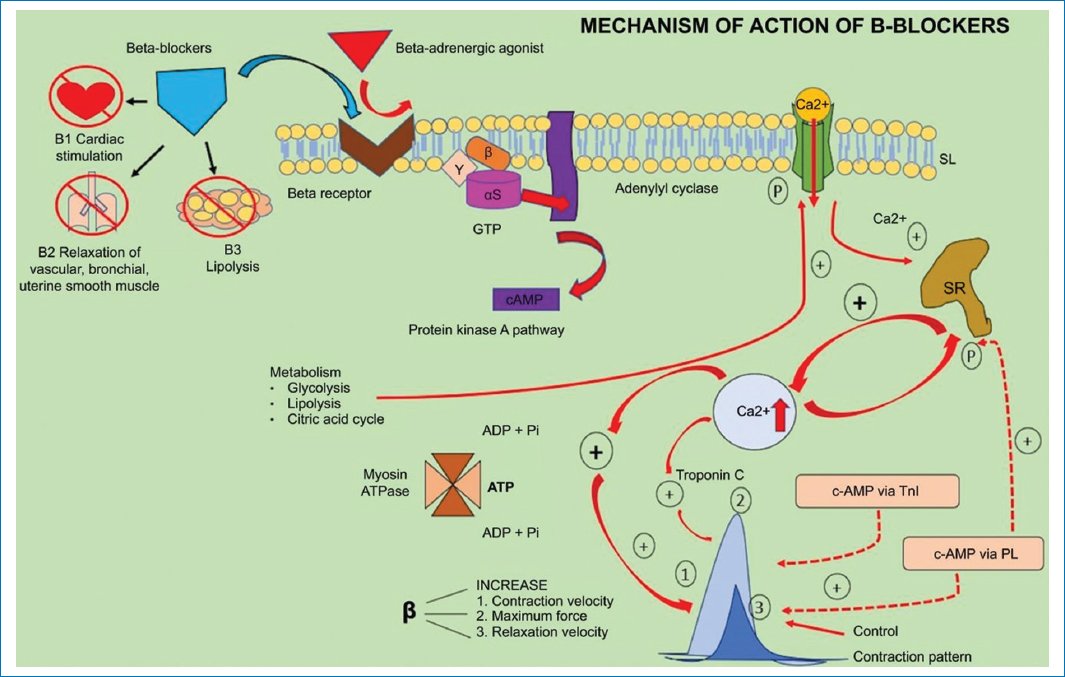
Figure 3. Mechanism of action of beta-blockers (Intracellular pathway mediated by adrenergic B receptors). (1) Catecholamines bind to B adrenergic receptors and induce coupling to the Gs protein. (2) Dissociation of the Gαs-GTP unit and activation of adenylyl cyclase. (3) Synthesis of cyclic adenosine monophosphate. (4) Activation of protein kinase A (PKA). Coordinated phosphorylation by PKA of several targets, such as the L-type calcium channel of the plasma membrane or the RyR2 calcium channel of the sarcoplasmic reticulum. (5) The result is an increase in cytosolic calcium (Ca2+) concentration available for cardiac muscle contraction and an increase in chronotropism.
Table 2. Classification of beta-blockers
| Variable | Activity | Medicine |
|---|---|---|
|
B1-B2 selective (Non-selective) |
Without vasodilatory activity |
Alprenolol Bupranolol Carazolol Oxprenolol Pindolol Propranolol Sotalol Timolol |
| B1 selective | With vasodilatory activity |
Carvedilol Labetalol |
| Without vasodilatory activity | Acetobotulol | |
| With vasodilatory activity |
Atenolol Betaxolol Bisoprolol Metoprolol Xamoterolol Celiprolol Nebivolol |
Systemic effects of propranolol
Through the blockade of β-adrenergic receptors, propranolol has been proposed as an effective strategy for reducing post-burn catabolism and, therefore, for improving outcomes in burn patients. Its effects are as follows:
Neurological
Beta-blockers prevent memory reconsolidation and have been administered to patients exposed to traumatic events to prevent post-traumatic stress syndrome.
However, studies in children and adults do not demonstrate that their administration reduces the incidence of post-traumatic stress syndromes or acute stress disorders.
Cardiac
It improves cardiac physiology and reduces cardiac stress in patients with severe burns.1 A 22% reduction in resting HR was observed after 2 weeks of propranolol treatment in burned adults.2
Skeletal muscle tissue
Propranolol has an effect on lean body mass. It improves protein kinetics in skeletal muscle with an improvement in net protein balance.10 On one hand, it increases the efficiency of protein synthesis in muscle by promoting the recycling of intracellular free amino acids. These intracellular amino acids derived from protein catabolism are re-incorporated into proteins without leaving the myocyte; on the other hand, it also stimulates the expression of genes involved in muscle metabolism and reduces the activation of genes involved (ubiquitin-proteasome system) in gluconeogenesis, thereby decreasing net catabolism2 (Fig. 4).
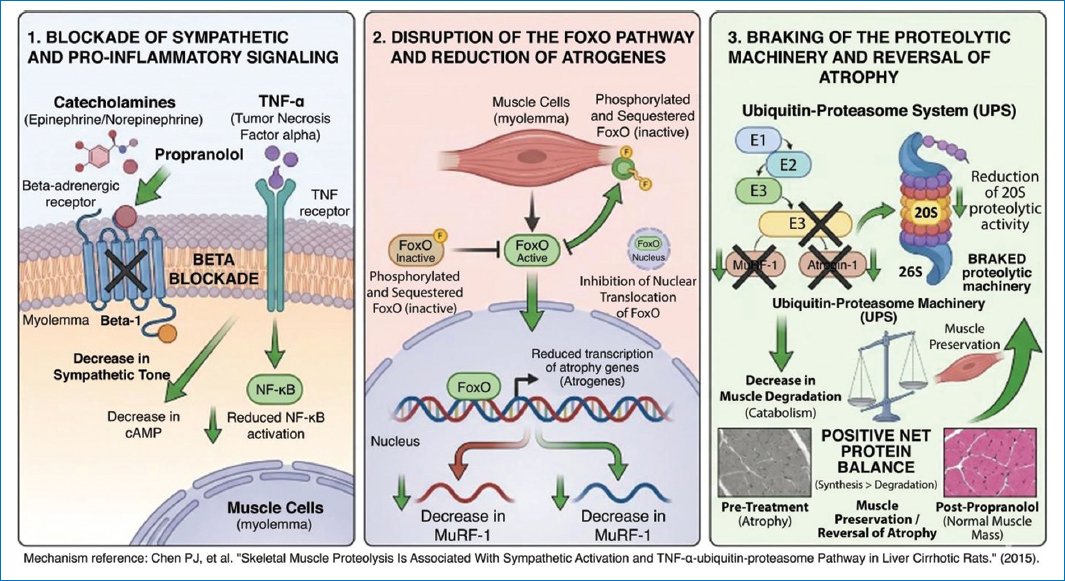
Figure 4. Mechanisms of propranolol as a “brake” on the ubiquitin-proteasome system.
Alterations in muscle protein kinetics continue after wound closure and discharge; short-term propranolol treatment also attenuates muscle wasting in patients with severe burns, primarily by increasing protein synthesis and the efficiency of muscle protein synthesis, while protein degradation remains unchanged.11
Therefore, addressing the loss of skeletal muscle to increase strength and function and to decrease physical and functional deterioration is of great importance for optimizing the recovery process and survival rates in victims of severe burns.
It is believed that the efflux of amino acids from skeletal muscle in response to a burn injury provides substrate for vital processes such as wound healing, immune function, and hepatic protein synthesis.12
Furthermore, propranolol improves the recycling of intracellular free amino acids by increasing the efficiency of protein synthesis in muscle, decreases peripheral lipolysis, and increases the efficiency of the liver in secreting free fatty acids13 (Fig. 5).
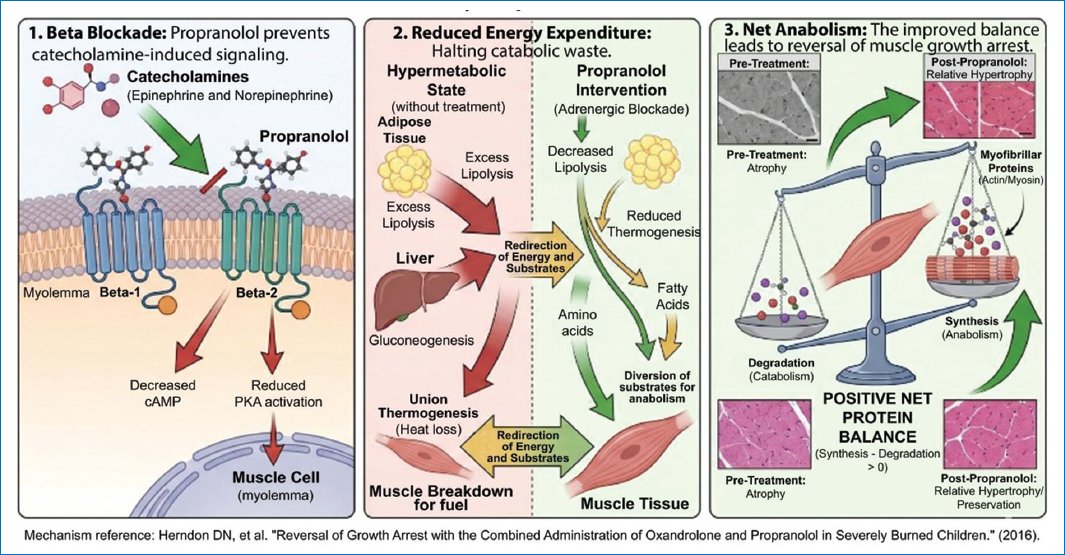
Figure 5. Protein preservation mechanisms of propranolol (anticatabolic mechanism).
Hematological
An important finding was that adults treated with propranolol required fewer blood transfusions. A possible explanation for this result is that the use of propranolol in cases of severe burns improves wound healing and therefore reduces the number of skin grafting procedures required.1
Hepatic and adipose tissue
The net fat balance through the liver is a function of the uptake of fatty acids from plasma, intrahepatic oxidation of fatty acids, and the release of triglycerides bound to very low-density lipoproteins (VLDL). Propranolol decreases the availability of free fatty acids for the liver. By decreasing the release of fatty acids from the periphery in the burn patient (peripheral lipolysis) and reducing splanchnic blood flow, it lowers the supply of fatty acids to the liver. Furthermore, it improves the conversion of free fatty acids into VLDL-bound triglycerides and their subsequent release from the liver. Therefore, propranolol has the beneficial effect of reducing hepatic fat accumulation in patients with burns, a common problem in this population.2
Wound healing and keratinocyte migration
Regarding wound healing, the total time for partial-thickness burns was notably shorter in patients receiving propranolol. In addition, donor site healing time was also shorter in the propranolol group.10
In one study, faster healing of superficial burns was noted in patients in the propranolol group. For superficial burns, less time was required for adequate healing: 13-15 days versus 20-22 days. Likewise, less time was required for patients with deep burns treated with propranolol to be ready for skin grafting: 23 days versus 33, compared with the control group.12
Pullar et al.14 identified a key regulatory mechanism in wound repair: the endogenous β-adrenergic receptor network in the epidermis. They demonstrated that the use of antagonists of these receptors, specifically of the β2 subtype, significantly accelerates the re-epithelialization of human cutaneous wounds.
The skin is not only a target of systemic hormones but also possesses its own catecholamine synthesis system. Human keratinocytes express high levels of β2-adrenergic receptors (β2-AR) and contain the enzymatic machinery necessary to synthesize epinephrine (adrenaline) endogenously.
- − Key enzymes: the presence of tyrosine hydroxylase, the rate-limiting enzyme in catecholamine biosynthesis, and phenylethanolamine-N-methyltransferase, which converts norepinephrine to epinephrine, was confirmed. These enzymes are located in cytoplasmic vesicles within keratinocytes.
- − Natural inhibitory function: the epinephrine synthesized by keratinocytes acts in an autocrine manner on β2-ARs, functioning as an “anti-motogenic” signal that normally slows cell migration.
- − Antagonist effect: by blocking these receptors with antagonists (such as timolol or the specific compound ICI 118,551), the inhibitory effect of endogenous epinephrine is neutralized, allowing cells to migrate more rapidly toward the wound bed.
Given that β-adrenergic antagonists are widely prescribed drugs known for their safety in the treatment of hypertension and glaucoma, their repositioning as topical or systemic agents for improving wound healing represents a promising therapeutic avenue. Pullar et al.14 conclude that blockade of β2-adrenergic receptors provides strong mechanistic support for new strategies aimed at accelerating cutaneous barrier repair in patients with impaired wound healing (Fig. 6).
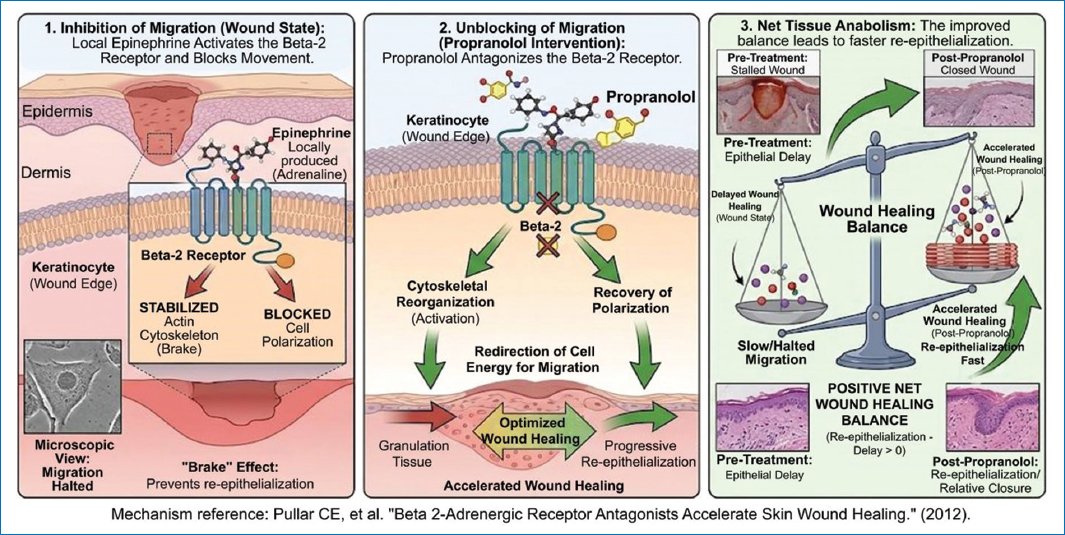
Figure 6. Mechanisms of propranolol as an adjuvant in keratinocyte migration and wound healing (“unblocking” mechanism).
Propranolol dosage
Neither the American Burn Association consensus nor the European Burns Association practice guidelines provide specific guidance on the use of beta-blockers or the optimal duration of their use. The European Society for Clinical Nutrition recommends the use of beta-blockers at the end of the 1st week after burn injury, but the duration of treatment is not defined6; it is effective when used at an adequate dose to reduce resting HR by 15-20% below the HR at admission. However, it is suggested that adult patients receive a standard dose of 20 mg every 6 h, increased as needed, although dosing studies in this population have not been conducted, and that treatment be initiated once patients have been stabilized with fluids, 24-72 h after admission.2 The kinetic profile of the extended-release capsule was similar to that of the liquid administered 4 times daily, despite being administered at a significantly lower dose.
Although the reduction in HR was lower in the every-24-h group than in the every-6-h group, it was not significant, indicating that the extended-release tablet is equally effective.3
Among its benefits, a significant decrease in length of hospital stay has been demonstrated in both adult patients and those treated with propranolol. This finding could be of great importance given that the management of the burn patient requires considerable financial resources.1
Complications
Although the use of propranolol in patients with severe burns can improve cardiac physiology, it is also associated with frequent episodes of hypotension and bradycardia¹, which can cause potentially life-threatening reactions such as pulmonary edema, shock, and complete heart block.9
The occurrence of colonic pseudo-obstruction (Ogilvie’s syndrome) has also been described in a patient treated with oral propranolol, who was successfully managed conservatively after propranolol withdrawal.2
Conclusion
Propranolol has been the drug used as a therapy to reduce the deleterious effects of the hypermetabolic response, with proven effectiveness. Our analysis indicates that the use of propranolol in patients with severe burns resulted in lower metabolic requirements at the multisystemic level. On the other hand, the evidence synthesized in this systematic review is limited to concluding that propranolol reduces the duration of hospital stay in patients with severe burns. Future trials must evaluate the impact of propranolol on clinically relevant outcomes, such as mortality and adverse events, as the available evidence requires further studies to confirm its effectiveness in both adult and pediatric patients.
Funding
The authors declare that no funding was received for this study.
Conflicts of interest
The authors declare no conflicts of interest.
Ethical considerations
Protection of human subjects and animals. The authors declare that no experiments on humans or animals were performed for this research.
Confidentiality, informed consent, and ethical approval. This study does not involve personal patient data, medical records, or biological samples, and does not require ethical approval. SAGER guidelines do not apply.
Declaration on the use of artificial intelligence. The authors declare that no generative artificial intelligence was used in the writing or creation of the content of this manuscript.
