
Introduction
Stroke is a clinical syndrome characterized by an acute neurological deficit of vascular origin.1 Globally, it represents the second leading cause of death and the third leading cause of combined death and disability.2 Hemorrhagic etiology has a critical clinical impact; specifically, intracerebral hemorrhage (ICH) accounts for 28.8% of all incident cerebrovascular events2 and is notable for its high mortality and the drastic deterioration it causes in quality of life.3,4 After surviving the acute event, patients frequently face chronic motor and functional deficits that are severely disabling.5,6
For the experimental study of ICH, intracortical microinjection of ferrous chloride (FeCl2) constitutes a widely used model due to its translational value, as it proportionally simulates the concentration of iron and the volume of extravasated blood during a clinical event in the human brain.7,8 Its validity is grounded in the Fenton and Haber-Weiss reactions, in which free iron induces highly cytotoxic hydroxyl radicals. These trigger lipid peroxidation, neuronal damage, and necrosis, simulating the effects of ICH.9–11
Pharmacological modulation has been proposed as a strategy to promote motor recovery after brain injury by regulating the neurochemical response.12,13 Early studies demonstrated that amphetamine administration facilitated functional recovery following stroke.14,15 Subsequently, attention shifted toward specific neurotransmitter systems involved in brain plasticity. Among these, norepinephrine (NE) has been extensively studied due to its role in regulating synaptic strength and neurogenesis.16–18 In this context, reboxetine has attracted interest as a pharmacological strategy, as it acts as a selective NE reuptake inhibitor.19–21 In fact, recent evidence in humans demonstrates that the noradrenergic increase induced by reboxetine significantly prolongs cortical neuroplasticity, positioning it as a highly promising therapeutic intervention for motor rehabilitation following stroke.22
Given the relevance of this neurotransmitter system, it is of interest to analyze structures with pronounced noradrenergic involvement. Among these, the pons stands out as the location of the locus coeruleus, the principal source of noradrenergic projections in the central nervous system.23,24 Equally important is the dentate gyrus of the hippocampus, a region involved in neuronal plasticity and adult neurogenesis, which has high innervation and adrenergic receptor expression.25–27 Furthermore, the loss of noradrenergic tone in these regions is linked to increased neuroinflammation and oxidative stress.28
In addition, diaschisis phenomena indicate that the functional consequences of brain damage are not confined to the site of the lesion but also affect regions anatomically and functionally connected to it.29,30 In parallel, following a lesion, compensatory mechanisms are activated that promote the reorganization of synaptic connectivity in surviving neurons, particularly in the contralateral hemisphere,31,32 a process in which noradrenergic modulation is crucial to facilitate motor recovery.33 Therefore, bilateral assessment of neurochemical changes is essential to identify the pathways involved in the therapeutic effects of reboxetine.
The objective of the present study was to evaluate the effect of acute and chronic reboxetine administration on sensorimotor function and NE levels in a model of intracortical injury induced by FeCl2 in young adult rats. Specifically, the degree of efficacy of sensorimotor recovery was compared between chronic and acute treatment regimens. As a complementary analysis, NE levels were quantified in the pons and the dentate gyrus, assessed both ipsilaterally and contralaterally to the lesion, to determine their relationship with the degree of sensorimotor deficit observed.
Material and methods
Experimental design and subjects
An experimental, prospective, controlled, and randomized study was conducted using 57 male Wistar rats (280-320 g), obtained from the animal facility of the Instituto Nacional de Neurología y Neurocirugía. Animal handling was carried out in accordance with the ethical principles of the Three Rs (replacement, reduction, and refinement), in compliance with the Official Mexican Standard NOM-062-ZOO-1999 and with the approval of the Institutional Committee for the Care and Use of Laboratory Animals (CICUAL-INNN 88/18). Animals were maintained under a reversed 12:12-h light-dark cycle, at an ambient temperature of 20-24°C and a relative humidity above 40%, with ad libitum access to water and food.
Subjects were assigned to four experimental groups for the acute protocol and four for the chronic protocol. Both regimens included two groups with FeCl2-induced lesions and two sham groups, subdivided according to reboxetine or vehicle administration. In the chronic protocol, animals were housed individually throughout the 10-day pretreatment period and received reboxetine (10 mg/kg) or drinking water. To ensure complete drug intake, the dose was dissolved in a volume of water 5 mL below the mean daily consumption previously determined for each animal. Solution homogeneity and waterer function were verified daily. In the acute protocol, animals received a single dose of reboxetine (10 mg/kg) or vehicle (3 mL of water) orally through esophageal cannula (16G × 3), 1 h after surgery.
Stereotaxic surgery
Animals were anesthetized with a combination of xylazine and ketamine (50 mg/kg each, i.p.) and received atropine sulfate (0.05 mg/kg, s.c.) to reduce respiratory secretions and prevent bradycardia. They were then placed in a stereotaxic frame. Before the incision, lidocaine (0.1 mL, i.d.) was infiltrated into the surgical area to provide local analgesia. Throughout the procedure, body temperature was maintained at 37°C using a thermal blanket. A craniotomy was performed for intracortical microinjection of 10 μL of FeCl2 (50 mM) or saline solution (sham groups) into the right primary motor cortex, specifically the area representing the contralateral hindlimb34 (Anteroposterior: −2.0 mm; mediolateral: −2.0 mm; and dorsoventral: −2.0 mm relative to bregma) at an infusion rate of 1 μL/min, with the purpose of inducing a focal hemorrhagic lesion.
On completion of the infusion, the surgical area was cleaned, the incision was sutured, and standard post-operative care was applied. Finally, topical nitrofurazone was applied to the ears, and isotonic saline solution (3 mL, i.p.) was administered to promote rehydration and anesthetic recovery.
Behavioral assessment
Behavioral evaluations were performed under double-blind conditions. Animals subjected to acute treatment were assessed at 3 time points: before surgery (Pre-sx), at day 1 post-surgery (1 DPS), and at day 3 post-surgery (3 DPS). Animals in the chronic protocol were assessed before treatment (Pre-tx), before surgery (Pre-sx), and at 1 DPS and 3 DPS.
Sensorimotor function was evaluated using the neurological scale modified by Pantoni.35 This test examines four functional domains: limb motor symmetry, grip strength, proprioception, and vibrissae tactile stimulus response. The total score ranges from 3 to 12 points, with higher values indicating less neurological impairment.
Spontaneous motor activity was quantified using the automated Auto-Track Opto-Varimex system (Columbus Instruments, Columbus, OH, USA) inside an anechoic chamber, as reported by Ramos-Languren et al.36 The variable analyzed was total distance traveled, expressed as a percentage relative to the presurgical baseline value.
Chromatographic analysis by high-performance liquid chromatography (HPLC)
Once behavioral evaluations were completed, animals were sacrificed for bilateral dissection of the pons and dentate gyrus. Samples were homogenized in an antioxidant solution composed of perchloric acid and sodium metabisulfite, using a volume equivalent to 20 times the tissue weight. They were subsequently centrifuged at 14,000 rpm for 20 min at 4°C, and the supernatant was recovered.
NE quantification was performed by HPLC coupled to electrochemical detection (Metrohm model 656, Switzerland). The system included an isocratic LC-250 pump (Perkin Elmer, Waltham, MA, USA), a Rheodyne valve, and a 20 μL injection loop. The mobile phase was composed of potassium monobasic phosphate (30 mM, pH 3.1), sodium octylsulfate (2 mM), ethylenediaminetetraacetic acid (1.6 mM), and HPLC-grade methanol at 16%, at a constant flow rate of 1 mL/min.
Chromatographic signals were integrated using TurboChrom (version 4.10) and Perkin-Elmer 1020 Plus software. NE concentration was determined by interpolation against a six-point standard curve (30-800 nM). Results were expressed as nmol of NE/g of fresh tissue, according to the procedure used by Ramos-Languren et al.36
Statistical analysis
Behavioral data were analyzed using a mixed analysis of variance (ANOVA) (within-subjects factor: time; between-subjects factors: lesion and treatment). Sphericity was assessed with Mauchly’s test, applying the Greenhouse-Geisser correction. NE concentrations were evaluated using an independent mixed ANOVA (within-subjects factor: hemisphere; between-subjects factors: lesion and treatment). Significant interactions were explored with Bonferroni post hoc tests. Subsequently, Spearman’s correlation was used to associate sensorimotor performance with NE levels. Data are presented as mean ± standard deviation in the results section. Statistical significance was set at p ≤ 0.05. The procedure is detailed in figure 1.
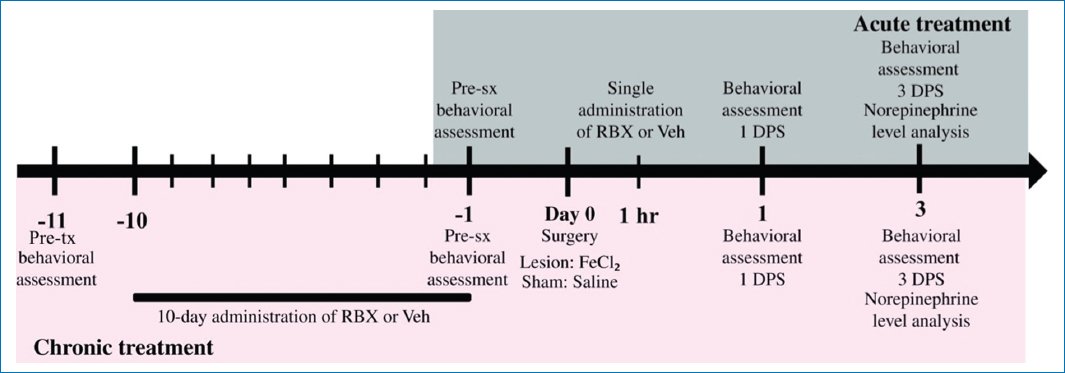
Figure 1. General procedure. For both treatment regimens, subjects were randomly assigned to four independent groups: Sham-Veh, Lesion-Veh, Sham-RBX, and Lesion-RBX. In the acute treatment (gray panel), following the pre-surgery behavioral assessment (Pre-sx) and stereotaxic surgery (day 0), a single dose of reboxetine or vehicle was administered 1 h after surgery. Behavior was subsequently assessed at 1 and 3 days post-surgery (1 and 3 DPS) before tissue extraction for chromatographic analysis. In the chronic treatment (pink panel), a pre-treatment assessment (Pre-tx) was conducted, after which reboxetine or vehicle was administered continuously for 10 days. At the end of this period, the Pre-sx assessment, surgery, and evaluations at 1 and 3 DPS were performed, concluding with tissue collection. FeCl2: ferrous chloride; RBX: reboxetine; Veh: vehicle.
Results
Behavioral assessment
In the sensorimotor evaluation of the group receiving acute single-dose treatment, significant interactions of time × lesion (F [2, 52] = 23, p < 0.001, η2p = 0.47) and time × treatment (F [2, 52] = 7.90, p = 0.001, η²p = 0.23) were observed. At the pre-surgery assessment, no differences were found between groups (p > 0.05). Following the lesion, both groups showed a significant decline in performance at 1 DPS compared with Sham groups (p < 0.001). At 3 DPS, reboxetine significantly reduced the sensorimotor deficit compared to vehicle (10.66 ± 0.34 vs. 8 ± 0.36; p = 0.001), matching the values of the Sham group (Fig. 2A). For the percentage of distance traveled, a main effect of time was found (F [2, 52] = 58.83, p < 0.001, η2p = 0.69), indicating a general decrease in locomotion after injury. Subsequently, reboxetine treatment increased locomotion compared to vehicle at 1 DPS (65.66 ± 5.98 vs. 30.73 ± 6.35; p < 0.001), a difference that was not maintained at 3 DPS (p > 0.05, Figs. 2B and C).
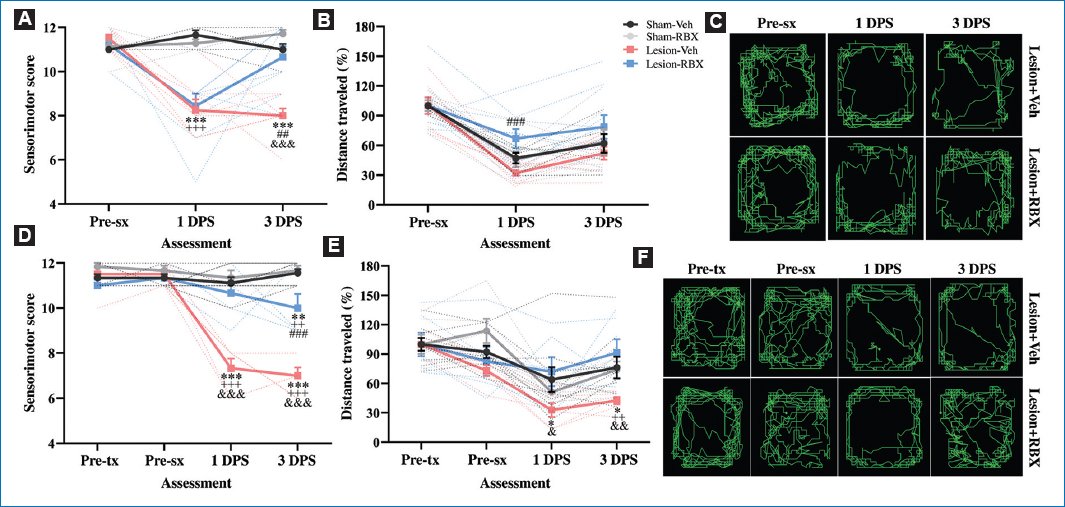
Figure 2. Effect of reboxetine on behavioral recovery following intracerebral hemorrhage. A: sensorimotor score, B: percentage of distance traveled during acute treatment, and C: representative images (control groups not shown) from the acute treatment group. D: sensorimotor score, E: percentage of distance traveled, and F: representative images (control groups not shown) during chronic treatment. Data express the mean ± SEM (solid lines) and individual values (dashed lines). Groups for acute treatment: Sham-Veh (black, n = 6), Sham-RBX (gray, n = 7), Lesion-Veh (red, n = 8), and Lesion-RBX (blue, n = 9). Groups for chronic treatment: Sham-Veh (n = 9), Sham-RBX (n = 6), Lesion-Veh (n = 6), and Lesion-RBX (n = 6). Pre-tx: pre-treatment; Pre-sx: pre-surgery; DPS: days post-surgery. Significant differences by time point: *vs. Sham-Veh; + vs. Sham-RBX; # vs. Lesion-Veh; & vs. Lesion-RBX. The number of symbols denotes the level of significance: one symbol p < 0.05, two symbols p < 0.01, three symbols p < 0.001.
On the other hand, in the sensorimotor evaluation of the chronic treatment group, a significant time × lesion × treatment interaction was found (F [3, 69] = 13.63, p < 0.001, η2p = 0.37). During the pre-treatment (Pre-tx) and pre-surgery (Pre-sx) phases, groups showed no differences (p > 0.05). Following the lesion, reboxetine attenuated the sensorimotor deficit compared to vehicle at 1 DPS (10.66 ± 0.39 vs. 7.33 ± 0.39; p < 0.001) and at 3 DPS (10 ± 0.38 vs. 7 ± 0.38; p < 0.001, Fig. 2D). For the percentage of locomotion, a time × lesion × treatment interaction was found (F [3, 69] = 4.90, p = 0.004, η2p = 0.18). Distance traveled during Pre-tx and Pre-sx did not differ between groups (p > 0.05). Subsequently, reboxetine treatment increased locomotion compared to vehicle at 1 DPS (72.06 ± 12.07 vs. 32.85 ± 12.07; p = 0.031) and at 3 DPS (91.36 ± 11.16 vs. 42.49 ± 11.16; p = 0.005, figures 2E and F).
Quantification of NE levels
For NE levels in the pons, the ANOVA showed a main group effect (F [3, 12] = 4.71, p = 0.02, η2p = 0.54). The hemisphere-level analysis showed that differences were limited to the side contralateral to the lesion (F [3, 12] = 6.25, p = 0.008, η2p = 0.61), with no significant changes in the ipsilateral hemisphere (p = 0.09). Post hoc tests indicated a reduction in the contralateral NE concentration in the lesion group compared to the control (Sham-Veh: 4.57 vs. Lesion-Veh: 2.06; p = 0.03), whereas reboxetine administration increased these levels when compared to its respective control group (Lesion-Veh: 2.06 vs. Lesion-RBX: 5.02; p = 0.01, Fig. 3A). In contrast, NE concentrations in the dentate gyrus showed no significant effects of group, hemisphere, or the group × hemisphere interaction (p > 0.05, Fig. 3B).
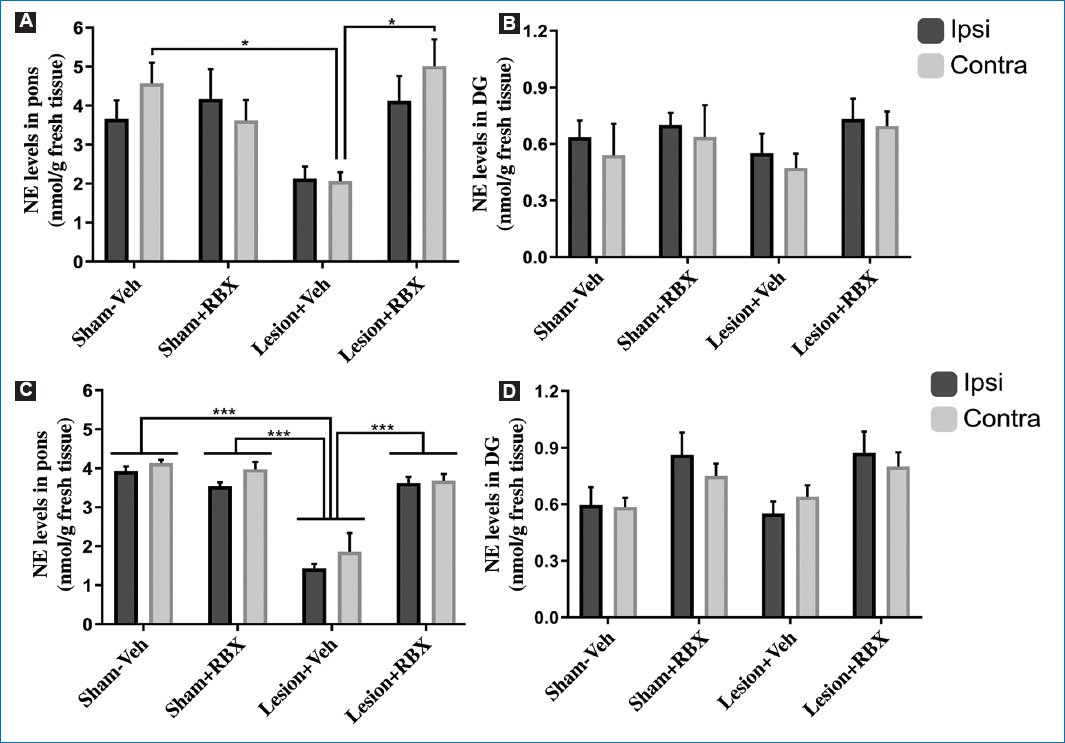
Figure 3. Effect of reboxetine on norepinephrine levels in the pons and dentate gyrus. Quantification of norepinephrine (nmol/g fresh tissue) in the ipsilateral and contralateral hemispheres relative to the lesion. A: upper panels correspond to acute treatment in the pons and B: dentate gyrus. C: lower panels show chronic treatment in the pons and D: dentate gyrus. Bars represent the mean ± Standard error of mean. *p < 0.05; ***p < 0.001. n = 4 per experimental group.
Under chronic treatment, the ANOVA showed a main group effect on pontine NE levels (F [3, 12] = 92.96, p < 0.001, η2p = 0.96), with no significant effects of hemisphere or the group × hemisphere interaction (p > 0.05). The absence of an interaction indicates that group differences occurred bilaterally. Post hoc comparisons showed that the Lesion-Veh group presented significantly lower global NE concentrations than the Sham-Veh (1.65 vs. 4.03; p < 0.001), Sham-RBX (1.65 vs. 3.76; p < 0.001), and Lesion-RBX (1.65 vs. 3.65; p < 0.001) groups (Fig. 3C).
In the dentate gyrus, a main group effect was also observed (F [3, 12] = 6.20, p = 0.01, η2p = 0.61); however, simple-effects analyses by hemisphere did not reveal statistically significant differences between groups (p > 0.05; Fig. 3D).
Association between NE levels and sensorimotor recovery
Under acute treatment, sensorimotor performance assessed at 3 days post-surgery showed a positive association with NE levels in the pons, both in the ipsilateral and contralateral hemispheres to the lesion (Figs. 4A and B). Similarly, under chronic treatment, sensorimotor performance positively correlated with NE levels in the contralateral pons, while a trend toward statistical significance was observed in the ipsilateral hemisphere (Figs. 4C and D). In contrast, no significant associations were found between behavioral variables and NE concentrations in the dentate gyrus.
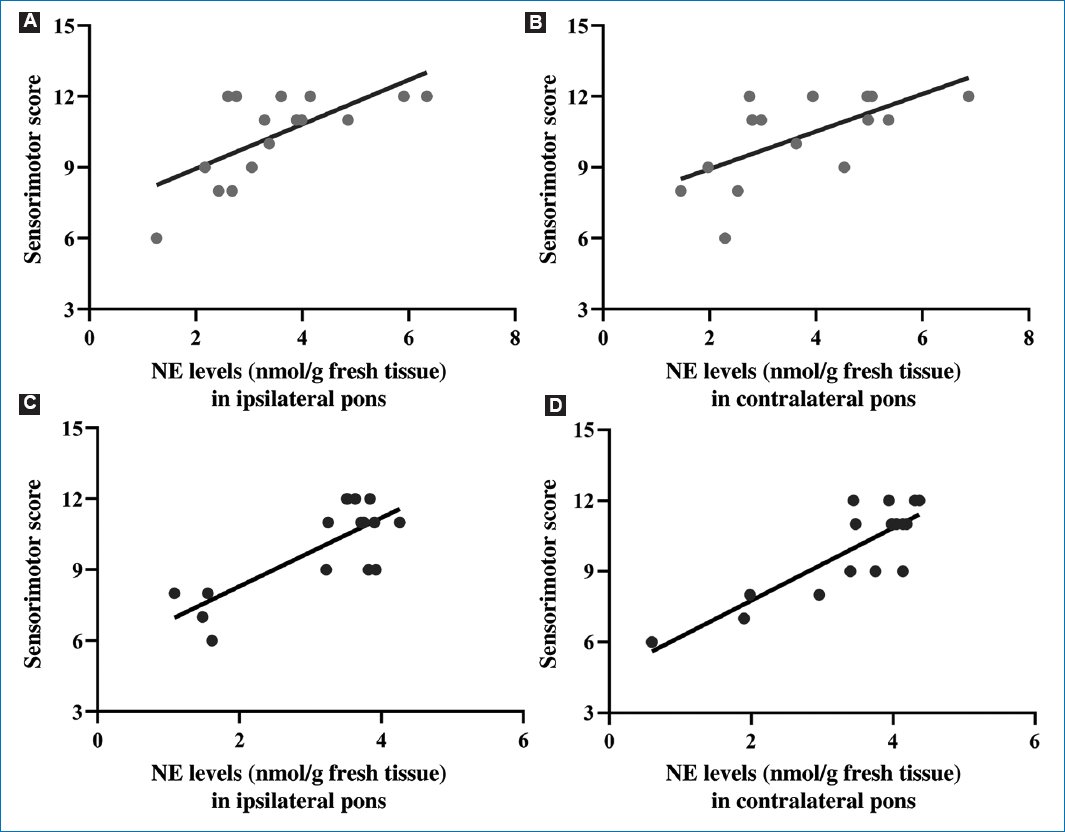
Figure 4. Association between norepinephrine levels and sensorimotor recovery. Spearman correlations between norepinephrine levels in the pons and sensorimotor performance at 3 days post-surgery. Upper panels (A and B: gray dots) correspond to acute treatment in the ipsilateral (rho = 0.63, p = 0.009) and contralateral (rho = 0.66, p = 0.005) regions, respectively. Lower panels (C and D: black dots) show chronic treatment on the ipsilateral (rho = 0.50, p = 0.050) and contralateral (rho = 0.72, p = 0.002) sides, respectively. n = 16 per treatment.
Discussion
ICH, one of the most severe forms of stroke, accounts for 28.8% of incident strokes2 and is associated with high mortality rates and marked deterioration of quality of life. Surviving patients frequently present persistent sensorimotor sequelae that significantly compromise their functionality and independence.5,6 In this context, it is essential to identify pharmacological strategies capable of promoting functional recovery and improving the prognosis of these patients.
The main finding of the present study was that reboxetine administration, a selective NE reuptake inhibitor, promoted sensorimotor recovery following FeCl2-induced cortical injury. Although both treatment regimens (acute and chronic) were effective in reversing the behavioral deficit, chronic administration produced earlier recovery than acute administration. This difference suggests that greater NE availability before the lesion facilitates the activation of adaptive mechanisms involved in functional recovery. This result is consistent with evidence identifying the noradrenergic system as a fundamental modulator of neuronal plasticity,22,37,38 a process indispensable for the dynamic reorganization of circuits and functional connections after cerebrovascular injury.24,39,40
The sensorimotor deficit observed at 3 DPS in lesioned animals was accompanied by a decrease in NE concentrations in the pons, suggesting that cortical injury generates neurochemical alterations that transcend the primary site of damage. This phenomenon can be interpreted in light of the diaschisis processes described following focal lesions, in which anatomically or functionally connected regions experience transient dysfunction secondary to the interruption of their connections.29,36,41,42 In this context, reboxetine administration prevented the NE decrease observed in lesioned animals, regardless of the therapeutic regimen employed, indicating an early restoration of noradrenergic neurotransmission.
The preservation of noradrenergic tone could constitute one of the mechanisms explaining the functional recovery observed. Reboxetine has been shown to potentiate and prolong forms of synaptic plasticity dependent on long-term potentiation in the cerebral cortex.22 Likewise, NE exerts its effects through the activation of adrenergic receptors widely distributed throughout the central nervous system.43 Through this interaction, NE is capable of modulating neurotransmitter systems such as glutamate,44 which are highly involved in the enhancement of synaptic plasticity and functional recovery.45 Collectively, this regulation of excitability constitutes a cellular mechanism that is fundamental for the reorganization of circuits affected by brain damage.38,40 In addition, noradrenergic signaling may promote the synthesis and release of brain-derived neurotrophic factor (BDNF), a molecule closely related to neuronal survival, synaptic plasticity, and functional recovery following brain injury.46
In contrast, no significant changes were detected in NE concentrations in the dentate gyrus during the first 3 days post-lesion. This result is consistent with previous studies reporting hippocampal monoaminergic changes at later stages of the recovery process.36 Taken together, these findings suggest that the early response to reboxetine primarily involves brainstem structures associated with the noradrenergic system, while hippocampal adaptations may develop in later phases.
Another relevant finding was the positive association between sensorimotor performance and NE concentrations in the pons, particularly in the contralateral hemisphere to the lesion. This relationship supports the involvement of the noradrenergic system in the mechanisms of functional recovery following cortical damage. Previous studies using the FeCl2 lesion model have shown that behavioral recovery is accompanied by restoration of noradrenergic neurotransmission and modifications in adrenergic receptor density.43 Given that the locus coeruleus constitutes the principal source of noradrenergic innervation in the brain, the changes observed in the pons could significantly influence circuits involved in functional reorganization following the lesion.
The relevance of the changes observed in the contralateral hemisphere is of particular interest in light of evidence indicating that non-lesioned regions contribute to the partial compensation of functional loss through processes of neuronal reorganization and the formation of new synaptic connections following a focal lesion.47,48 For this reorganization to occur, NE regulates various cellular mechanisms related to neuronal plasticity, including neuronal excitability, activity-dependent gene expression, and the strengthening of synaptic connections.16,22 In particular, noradrenergic activation promotes BDNF expression,46 a neurotrophin closely linked to functional recovery processes. Recently, it has been demonstrated that activation of the BDNF-Tropomyosin receptor kinase B signaling pathway and its intracellular cascades promotes neuronal survival, regulates circuit excitability, and favors axonal regeneration following ischemic injury, significantly contributing to the recovery of motor function.49
Despite the relevance of these findings, the present study has some limitations that must be considered. Neurochemical evaluation was conducted only during the early phase of recovery; therefore, it is not possible to determine whether the observed changes in noradrenergic neurotransmission persist into later stages. Furthermore, changes in adrenergic receptor expression, neuronal plasticity markers, or neurotrophic factors were not analyzed—variables that could contribute to clarifying the mechanisms underlying the effects of reboxetine. Future research should therefore examine the temporal evolution of these neurochemical and molecular adaptations, as well as the possible late involvement of the dentate gyrus and other structures related to plasticity and functional recovery.
Conclusion
The present study provides evidence of the behavioral and neurochemical responses that occur following intracortical injury induced by FeCl2. Our results show that reboxetine administration promotes sensorimotor recovery, with the chronic regimen being more effective at accelerating functional improvement from the early stages following the lesion. Moreover, a positive association was observed between sensorimotor performance and NE concentrations in the pons, suggesting that preservation of noradrenergic neurotransmission constitutes a relevant mechanism in functional recovery.
Taken together, these findings indicate that NE availability plays a key role in the compensatory plasticity processes that follow cortical damage and support the therapeutic potential of noradrenergic modulation to promote neurological recovery. In addition, this research broadens the understanding of neurochemical alterations induced by experimental vascular lesions and provides a conceptual foundation for the development of future pharmacological strategies aimed at enhancing endogenous brain repair mechanisms.
Data availability
The datasets generated and analyzed during the current study are publicly available in the Open Science Framework (OSF) repository: https://doi.org/10.17605/OSF.IO/V54FA.
Funding
The authors declare that this study was funded by PAPIIT-UNAM under grant IN216221. I. Saucedo-Flores received a scholarship from the Consejo Nacional de Ciencia y Tecnología (CONACYT), Mexico (CVU 1084617).
Conflicts of interest
The authors declare no conflicts of interest.
Ethical considerations
Protection of persons and animals. The authors declare that the experimental procedures were carried out in accordance with the Official Mexican Standard (NOM-062-ZOO-1999) and under the approval of the Institutional Ethics Committee (CICUAL-INNN 88/18).
Confidentiality, informed consent, and ethical approval. This study does not involve personal patient data, medical records, or biological samples, and does not require ethical approval. SAGER guidelines do not apply.
Declaration on the use of artificial intelligence. The authors declare having used a generative artificial intelligence tool, specifically Gemini and Copilot, solely as technical assistance: to verify statistical syntax in SPSS, resolve operational questions in Affinity, and perform minor grammatical revisions. The scientific conception and original writing are exclusively the work of the authors. They likewise declare having thoroughly reviewed the manuscript and assume full responsibility for the accuracy and integrity of the final content.
