
Introduction
Nursing personnel constitute one of the most important pillars of healthcare systems, as they provide direct and continuous patient care throughout all stages of the healthcare process, particularly in oncology services. Their work requires not only solid professional training but also a high degree of emotional commitment1,2. Working conditions, such as prolonged shifts, excessive workload, staff shortages, and constant exposure to pain, suffering, and death increase the risk of progressive deterioration of both physical and mental well-being3,4.
In this context, burnout syndrome (BS) has been identified as one of the major occupational health concerns affecting healthcare professionals. This syndrome is characterized by a negative emotional response to chronic workplace stress and is manifested through three dimensions: emotional exhaustion (EE), defined as feelings of extreme fatigue and loss of energy; depersonalization (DP), characterized by a detached attitude toward patients; and reduced personal accomplishment (PA)5–7.
Numerous studies have demonstrated that BS affects not only the psychological health of healthcare workers but also the quality of care, patient safety, and organizational stability8,9. Data from Mexico, including reports from the Instituto Mexicano del Seguro Social (IMSS), indicate that even before the coronavirus disease-2019 pandemic, Mexico ranked among the countries with the highest levels of occupational stress-related fatigue. Approximately 75% of workers experienced this condition, exceeding the rates reported in countries, such as China (73%) and the United States (59%)10. Furthermore, burnout has been associated with higher rates of absenteeism, staff turnover, and reduced work performance, resulting in both human and economic consequences for healthcare institutions11,12. Consequently, addressing burnout has become a priority challenge for contemporary healthcare systems.
Several factors significantly increase the emotional vulnerability of oncology nursing personnel and contribute to both the development and severity of BS. These include age, sex, years of professional experience, marital status, and number of children, all of which influence how individuals cope with occupational demands13–15.
In addition, the lack of institutional policies focused on protecting nurses’ mental health exacerbates this problem. Healthcare organizations often prioritize clinical outcomes, thereby perpetuating environments characterized by constant stress16,17. Burnout is not merely an individual issue but an organizational phenomenon that compromises service quality1 and patient safety18–21.
The identification and assessment of burnout among nursing personnel provides valuable evidence for the design of preventive and corrective strategies tailored to the actual needs of this professional group, particularly in oncology settings. Therefore, the aim of this study was to determine the prevalence of BS and its associated factors among oncology nursing staff working in a tertiary-care hospital of the IMSS in Puebla, Mexico.
Material and methods
A descriptive cross-sectional study was conducted among nursing personnel working different shifts in the Oncology Department of a tertiary-care hospital belonging to the IMSS in Puebla, Mexico. Eligible participants included permanent nursing staff assigned to the oncology service, with at least 1 year of employment at the institution, who voluntarily agreed to participate and provided written informed consent.
The following variables were assessed: sex, age, work shift, educational level, professional experience, number of children, marital status, overtime work, number of patients attended per shift, availability of psychological support, and the presence of BS.
BS was evaluated using the Mexican-adapted version of the Maslach Burnout Inventory (MBI)8. The instrument consists of 22 items scored on a Likert-type scale ranging from “never” to “every day” and assesses three domains: EE EE, DP, and PA.
Data were analyzed using the Statistical Package for the Social Sciences, version 25 for Windows. The reliability of the MBI was assessed using Cronbach’s alpha coefficient. Descriptive statistics were applied, and study findings were summarized through frequencies and percentages.
The study was approved by the Health Research Committee No. 2101 of the IMSS. All participants provided written informed consent before enrollment. Data were handled with strict confidentiality and used exclusively for research purposes. Participants identified as presenting BS were referred to the institution’s Occupational Health Service for further evaluation and support.
Results
A total of 71 nurses were evaluated, of whom 37 presented findings consistent with BS, yielding a prevalence of 52.1%. Most participants were female (86.1%). The most frequent age group was 31-40 years, accounting for 58.4% of the sample. Regarding work shifts, 50% worked the morning shift. Technical-level education was reported by 44.4% of participants, while 53.3% had between 6 and 15 years of professional experience. Concerning personal characteristics, 55.6% had three or more children, and 52.8% were married. Overtime work was reported by 69.4% of the participants, and 61.2% attended between 11 and 18 patients per shift. Furthermore, 88.9% reported having no access to psychological support services (Table 1).
Table 1. Sociodemographic characteristics of oncology nursing personnel
| Variable | Category | n | % |
|---|---|---|---|
| Sex | Female | 32 | 86.1 |
| Male | 5 | 13.9 | |
| Age | 25-30 years | 3 | 8.3 |
| 31-40 years | 22 | 58.4 | |
| ≥ 41 years | 12 | 33.3 | |
| Work shift | Morning | 18 | 50 |
| Evening | 12 | 33.3 | |
| Night | 6 | 16.7 | |
| Educational level | Technical degree | 16 | 44.4 |
| Bachelor’s degree | 15 | 41.7 | |
| Postgraduate degree | 5 | 13.9 | |
| Professional experience | 1-5 years | 11 | 28.9 |
| 6-15 years | 20 | 53.3 | |
| > 15 years | 6 | 17.8 | |
| Number of children | 1-2 children | 16 | 44.4 |
| > 3 children | 20 | 55.6 | |
| Marital status | Married | 19 | 52.8 |
| Single | 17 | 47.2 | |
| Overtime work | Yes | 25 | 69.4 |
| No | 11 | 30.6 | |
| Patients attended per shift | 11-18 patients | 22 | 61.2 |
| > 20 patients | 6 | 16.6 | |
| Psychological support | Yes | 4 | 11.1 |
| No | 32 | 88.9 |
The MBI demonstrated adequate internal consistency. Cronbach’s alpha coefficients were 0.846 for EE, 0.602 for DP, and 0.705 for PA.
Regarding EE, 40.5% of participants perceived that they were working excessively, while 24.3% considered their work emotionally draining. In the DP dimension, most participants did not exhibit depersonalizing attitudes toward patients; 73.0% reported that they never treated patients as impersonal objects. In the PA dimension, 75.6% indicated that they frequently created a positive and pleasant work environment (Table 2).
Table 2. Main findings by dimension according to the Maslach Burnout Inventory
| Burnout dimension | Item | % |
|---|---|---|
| Emotional exhaustion | Perceives working excessively | 40.5 |
| Feels exhausted several times per week | 32.4 | |
| Feels tired at the end of the workday | 27.0 | |
| Feels fatigued at the beginning of a new shift | 27.0 | |
| Considers work emotionally draining | 24.3 | |
| Depersonalization | Never treats patients as impersonal objects | 73.0 |
| Always cares about what happens to patients | 54.1 | |
| Feels that work is making them emotionally hardened | 27.1 | |
| Acknowledges becoming more insensitive over time | 16.3 | |
| Personal accomplishment | Frequently creates a positive work environment | 75.6 |
| Can easily understand patients’ needs and feelings | 64.9 | |
| Effectively manages daily problems and positively influences others | 48.7 | |
| Feels highly energetic | 27.0 | |
| Feels appreciated after work | 24.3 |
Overall, EE showed a high level of burnout in 47.8% of participants. This proportion, representing nearly half of the sample, together with the 28.2% classified as having a moderate level, indicates that most professionals (76.0%) experienced considerable degrees of EE. DP scores were primarily distributed between low and moderate levels. Although 46.4% of participants were classified as having low DP, a substantial proportion (42.4%) fell within the moderate category. The most severe manifestation (high level) was observed in 11.2% of participants.
PA showed predominantly favorable results, with 77.4% of respondents reporting high levels of accomplishment (Fig. 1).
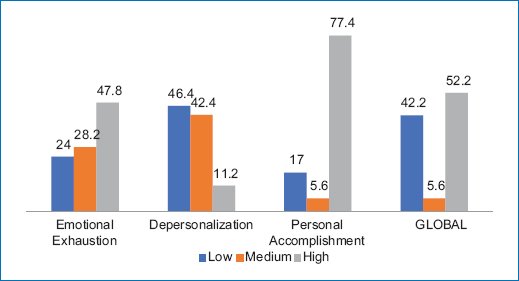
Figure 1. Results of the Maslach Burnout Inventory. Global and dimensional percentages of burnout syndrome among oncology nursing personnel (n = 71).
The overall assessment of BS revealed a polarized distribution among the study population. Of particular relevance, more than half of the participants (52.2%) were classified as having a high level of BS (Fig. 1).
Discussion
The primary objective of this study was to assess BS levels among nursing personnel working in a highly demanding clinical setting, such as oncology services, where both physical and emotional demands are substantial and persistent.
Most participants were women, predominantly aged between 31 and 40 years, and more than half reported over 6 years of professional experience. These findings are consistent with previous reports22, which describe a similar nursing workforce profile characterized by female predominance and exposure to a dual workload that intensifies occupational stress. Furthermore, the high proportion of staff performing overtime work and the lack of use of institutional psychological support highlight the absence of effective preventive measures against professional exhaustion.
Among the dimensions of BS, EE was the most affected. This finding represents a significant risk factor and suggests a critical need for preventive interventions. Previous studies have identified EE as the core component of burnout and have linked it closely to excessive workload and insufficient organizational resources22.
In addition, 53.6% of participants reported moderate or high levels of DP. Although severe emotional detachment was relatively uncommon, feelings of emotional distancing and a detached attitude toward work were recurrent experiences. In contrast, PA showed a predominantly favorable profile, indicating that most professionals maintained a strong sense of achievement and purpose in their work. This finding contrasts markedly with the high levels of EE and underscores the persistence of professional commitment despite substantial fatigue.
A considerable proportion of participants (58%) reported experiencing BS at moderate-to-high intensity, a finding that warrants priority attention. These results are consistent with those reported by Ramírez-Pérez and Osorio-Guzmán21 who studied Mexican healthcare professionals working in public oncology services and found moderate or high burnout levels in more than 60% of participants, while 100% reported high levels of PA.
Similarly, the present study identified a comparable pattern: despite the predominance of EE, most participants reported high levels of PA, reflecting substantial resilience among oncology nursing professionals.
However, contextual differences were observed between both populations. In the study by Ramírez-Pérez and Osorio-Guzmán21, the mean age was 45 years and average job tenure approached 14 years. In contrast, the present sample consisted predominantly of younger professionals (31-40 years), facing heavy clinical workloads and perceiving limited psychological support. These conditions may contribute to greater vulnerability to occupational exhaustion, adversely affecting both mental health and professional performance. Notably, mental health services for healthcare workers within the IMSS have recently undergone significant strengthening and optimization.
These findings further support the notion that, despite experiencing substantial occupational strain, healthcare workers maintain a strong sense of professional commitment and job satisfaction. The ability to preserve a sense of purpose under continuous pressure may function as a protective factor against DP and occupational cynicism. This observation is consistent with previous evidence suggesting that vocational commitment and satisfaction derived from patient care act as coping mechanisms that mitigate the negative effects of BS22–24.
This positive dimension has also been associated with adaptive capacity and ethical commitment to patients, enabling healthcare professionals to maintain motivation and a sense of usefulness even under conditions of considerable EE25–27.
The results of the present study are consistent with previous reports (8.21) indicating that BS among nursing personnel is a multifactorial, persistent, and complex phenomenon influenced by organizational, emotional, and personal factors. Excessive workload, insufficient psychological support, and limited institutional resources emerged as the principal contributors to EE28–30.
Conclusion
The prevalence of BS symptoms among oncology nursing personnel reflects a multifactorial problem primarily associated with excessive workload, the emotional demands inherent to patient care, and workplace interpersonal dynamics. Rather than indicating a lack of professional commitment, the challenge appears to stem from the absence of effective strategies to mitigate EE.
Therefore, strengthening institutional policies aimed at improving working conditions, redistributing clinical workloads, and implementing permanent psychological support programs is essential to protect the health and well-being of nursing personnel.
Given this scenario, the implementation of intervention programs designed to promote healthy work environments, improve work–life balance, and strengthen resilience as a coping strategy is urgently needed19,20.
Funding
The authors declare that they have not received funding.
Conflicts of interest
J. Loría-Castellanos is a member of the editorial board of the journal Anales Médicos. The others authors declare no conflicts of interest.
Ethical considerations
Protection of human subjects and animals. The authors declare that no experiments on humans or animals were performed for this research.
Confidentiality, informed consent, and ethical approval. The authors have followed their institution’s confidentiality protocols, obtained informed consent from all patients, and secured approval from the Ethics Committee. SAGER guidelines have been followed as applicable to the nature of the study.
Declaration on the use of artificial intelligence. The authors declare that no generative artificial intelligence was used in the writing or creation of the content of this manuscript.
